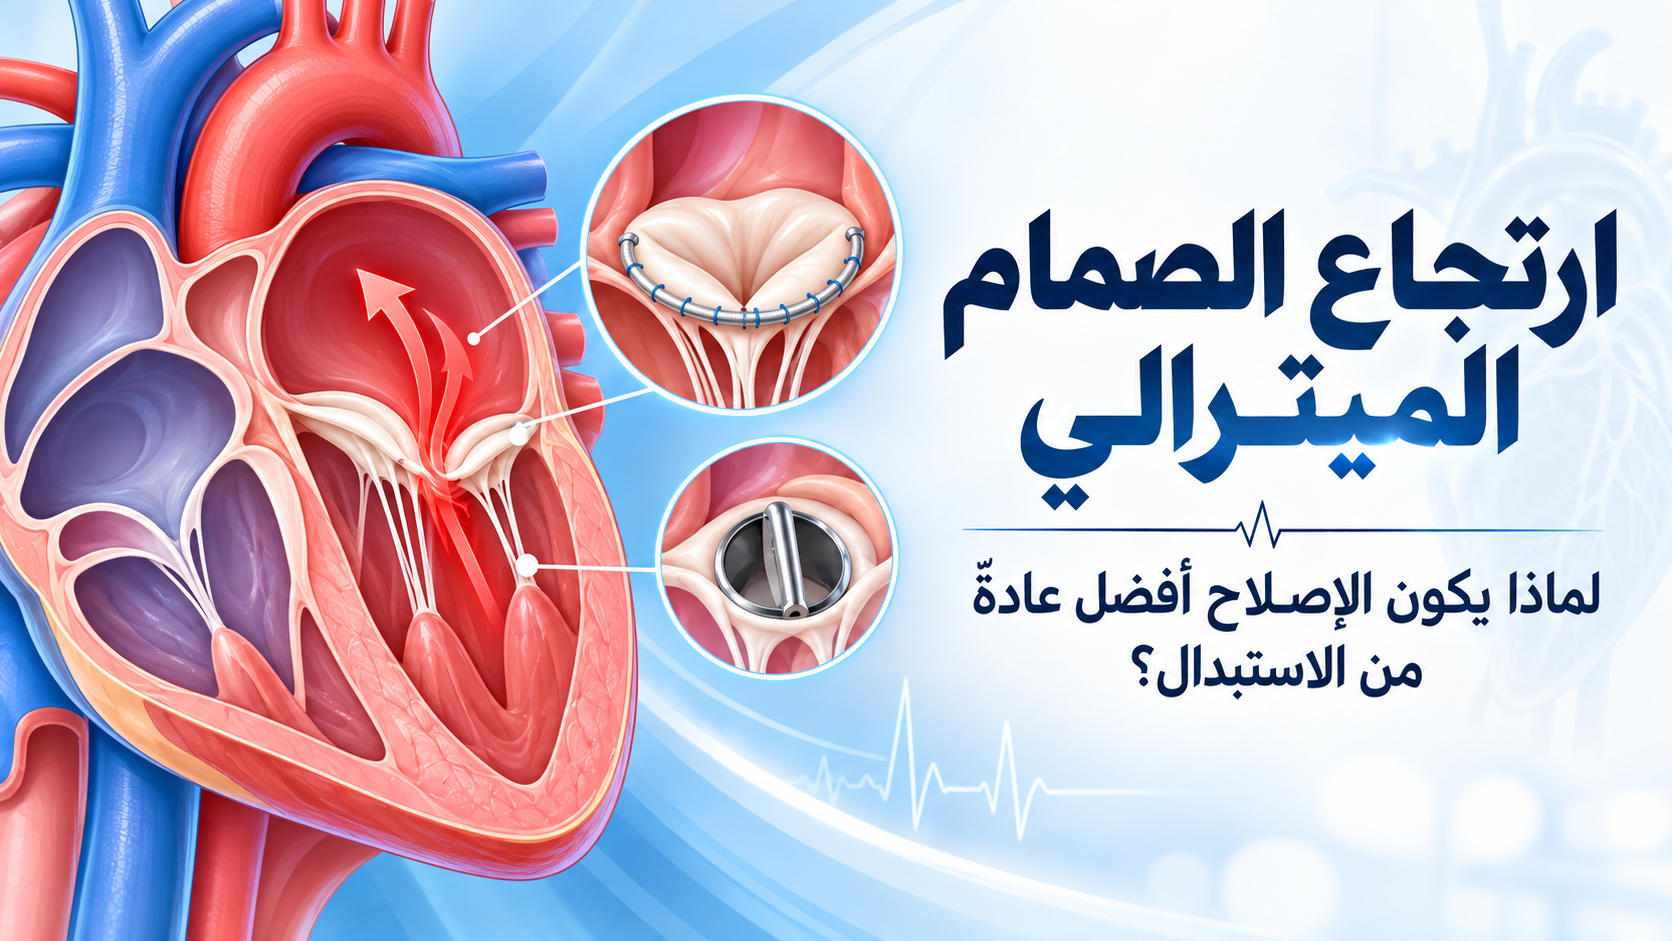
Mitral Valve Regurgitation: Why Repair Is Usually Better Than Replacement
What goes wrong
The mitral valve sits between the left atrium and the left ventricle. It should close completely when the ventricle contracts, so that all the blood is driven forward into the aorta. In mitral regurgitation it does not close properly, and a portion of each beat leaks backwards into the atrium.
The consequence is inefficiency: the heart must handle the same blood twice. The left atrium stretches to accommodate the returning volume, and the left ventricle enlarges as it works harder to maintain forward output.
Two very different causes
Primary (degenerative)
The valve apparatus itself is diseased — leaflets that prolapse, elongated or ruptured chordae, or a dilated annulus. Mitral valve prolapse is the commonest form. Here the valve is the problem, and fixing the valve fixes the disease.
Secondary (functional)
The leaflets are structurally normal, but the ventricle has enlarged — usually after a heart attack or in cardiomyopathy — pulling the valve apparatus apart so it can no longer close. Here the valve is a victim rather than the cause, and treatment must address the underlying ventricular disease as well.
This distinction drives everything that follows, because the two behave differently and respond differently to surgery.
Symptoms and the trap of feeling well
Mitral regurgitation develops slowly and the heart compensates, so patients often feel well for years. When symptoms come they include breathlessness on exertion and then when lying flat, fatigue, palpitations — atrial fibrillation is common once the atrium enlarges — and eventually leg swelling.
The trap is this: by the time a patient feels clearly unwell, the ventricle may already have suffered damage that surgery cannot undo. That is why patients with known significant regurgitation are followed with regular echocardiograms even while symptom-free, watching ventricular size and function rather than waiting for complaints.
Diagnosis
A systolic murmur is the usual first sign. Echocardiography grades severity, establishes the mechanism, and measures its effects on chamber size, pumping function and pulmonary pressures. Transoesophageal echocardiography gives a far more detailed view of the valve and is central to planning repair — it defines exactly which segment is prolapsing and whether repair is feasible.
Why repair beats replacement
For primary degenerative disease, repair is clearly preferable where it is achievable and durable:
- It preserves the natural attachments between the valve and the ventricle, which matter for how the ventricle contracts. Cutting them, as replacement historically did, reduces ventricular performance.
- It usually avoids lifelong anticoagulation.
- It carries a lower risk of prosthetic infection.
- Long-term survival after successful repair is better than after replacement in comparable patients.
Replacement remains the right answer when the valve is too destroyed, heavily calcified, or rheumatic in a way that will not give a durable repair — a poor repair is not preferable to a good replacement. Where replacement is needed, the prosthesis choice matters; see mechanical or tissue valve.
Surgical approach
Repair techniques include resecting or re-suspending prolapsing segments, replacing chordae with artificial ones, and supporting the valve with an annuloplasty ring.
The mitral valve is particularly suited to minimally invasive access — through a small incision between the ribs on the right side, often with video assistance, rather than dividing the breastbone. Randomised work comparing this with conventional sternotomy has shown longer operating times but shorter intensive care and hospital stays, less blood loss, less pain and better early respiratory function. Suitability still depends on the individual anatomy and previous surgery.
For selected patients at high surgical risk, transcatheter edge-to-edge repair offers a catheter-based alternative.
What to ask before surgery
- Is my valve repairable, and what is the expected likelihood of a durable repair?
- Is my regurgitation primary or secondary?
- Has my ventricle already changed, and does that affect timing?
- Is a minimally invasive approach suitable for me?
Further reading
NHS: mitral valve problems and MedlinePlus: heart valve diseases.
On this site: valve surgery, and published research including randomised studies of minimally invasive mitral surgery.
General education, not advice about your own valve. Whether repair is possible depends on your echocardiographic findings and must be assessed individually.