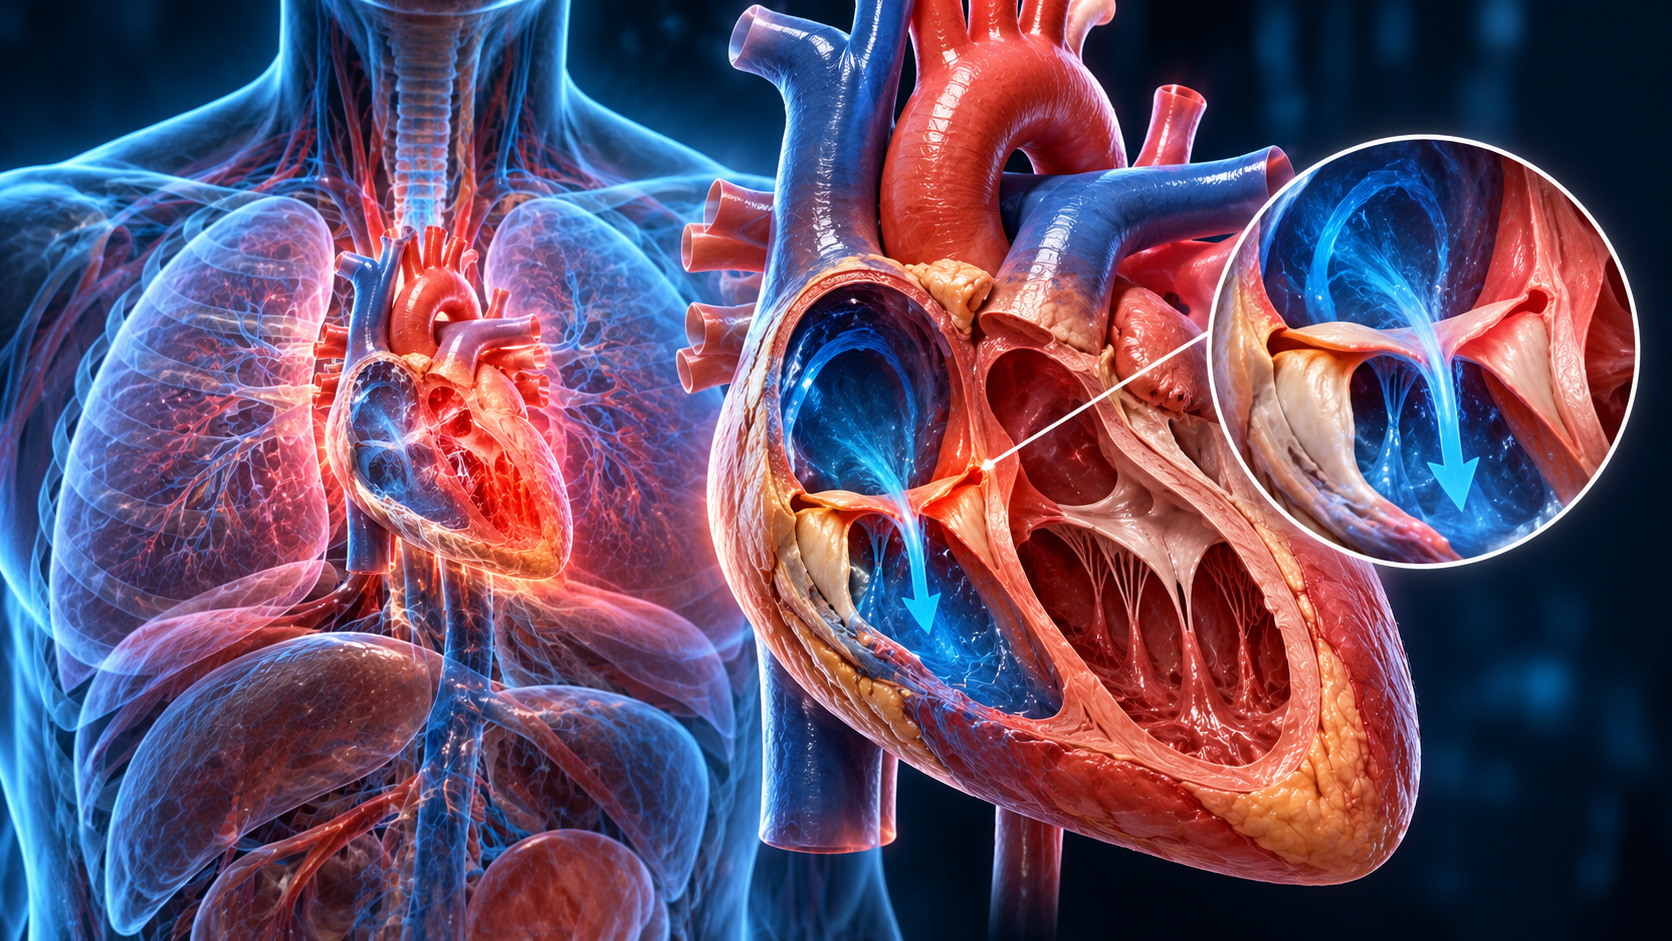
Tricuspid Valve Disease: The Forgotten Valve of the Heart
Why it earned that name
The tricuspid valve sits between the right atrium and the right ventricle. For decades it was called the forgotten valve, for two reasons: its disease is usually a consequence of something else rather than a primary problem, and its symptoms are easily attributed to other causes.
That neglect is no longer considered acceptable, and understanding why is the point of this article.
Primary and secondary disease
Secondary (functional) — the large majority
The leaflets themselves are structurally normal. The problem is that the right ventricle and the valve ring have dilated, pulling the leaflets apart so they can no longer meet.
Why does the right side dilate? Almost always because of pressure transmitted backwards from the left side of the heart — most often from mitral valve disease — or from pulmonary hypertension, or from right ventricular disease itself. The tricuspid valve is a victim of a problem elsewhere.
Primary — less common
The valve itself is diseased: infective endocarditis, particularly in intravenous drug use, which characteristically affects this valve; rheumatic disease; trauma; damage from pacemaker or defibrillator leads crossing the valve; carcinoid disease; and congenital abnormalities such as Ebstein anomaly.
Symptoms that get blamed on something else
Left-sided valve disease causes breathlessness, which points clearly at the heart. Tricuspid regurgitation causes congestion in the body's veins instead, and those symptoms are far less obviously cardiac:
- Swelling of the legs and ankles, often attributed to standing, salt or age;
- Abdominal swelling and a sense of fullness or bloating;
- Enlarged, tender liver — sometimes investigated as a primary liver problem;
- Loss of appetite and early satiety, from congestion of the gut;
- Visible pulsation in the neck veins;
- Fatigue, which is often the dominant complaint;
- Later, fluid in the abdomen and progressive liver dysfunction.
Patients with significant tricuspid regurgitation are not uncommonly investigated by gastroenterology or hepatology before the heart is considered. Fatigue with leg and abdominal swelling and a large liver deserves an echocardiogram.
Why it was under-treated — and why that changed
The old reasoning ran: since the leak is secondary, fix the left-sided problem and the right side will recover on its own. Sometimes it does. Frequently it does not.
Once the right ventricle and the valve ring have dilated beyond a certain point, the changes become self-sustaining. The leak keeps volume-loading the right ventricle, which dilates further, which worsens the leak. Correcting mitral disease alone leaves that cycle running.
The consequence has been well documented: patients returning years after successful left-sided surgery with severe tricuspid regurgitation, right heart failure and liver congestion. Reoperating on the tricuspid valve in that situation carries substantially higher risk than treating it at the original operation.
Modern practice therefore favours addressing significant tricuspid regurgitation — and a dilated valve ring even when the leak looks moderate — at the time of left-sided surgery. Adding a repair costs relatively little operative time and avoids a far harder second operation.
Diagnosis
Echocardiography grades the leak, measures the valve ring, and assesses right ventricular size and function and pulmonary artery pressure — and it is that combination, not the leak alone, that drives decisions. Right ventricular function is notoriously difficult to assess, so cardiac MRI is increasingly used. Liver function tests and abdominal imaging show the downstream consequences.
Treatment
- Medical — diuretics relieve congestion and treatment is directed at the underlying cause, but medication does not correct the valve.
- Repair — the preferred surgical option, usually by annuloplasty: placing a ring to restore the valve ring to its proper size so the leaflets meet again.
- Replacement — where the valve is structurally destroyed, as in endocarditis or advanced rheumatic disease.
- Transcatheter treatment — an evolving option for high-risk patients unsuitable for surgery.
Timing follows the same principle that governs all valve surgery: intervening before the ventricle is irreversibly damaged. Once the right ventricle and liver are severely affected, results are markedly worse — which is the whole argument for not leaving this valve to last.
Further reading
MedlinePlus: heart valve diseases and guidelines from the European Society of Cardiology.
On this site: valve surgery.
General education, not advice about your own valve. Persistent leg or abdominal swelling with fatigue should be assessed medically rather than attributed to age.